
Check the drug, indication and trial behind your holding before treating the historical average as your own probability.
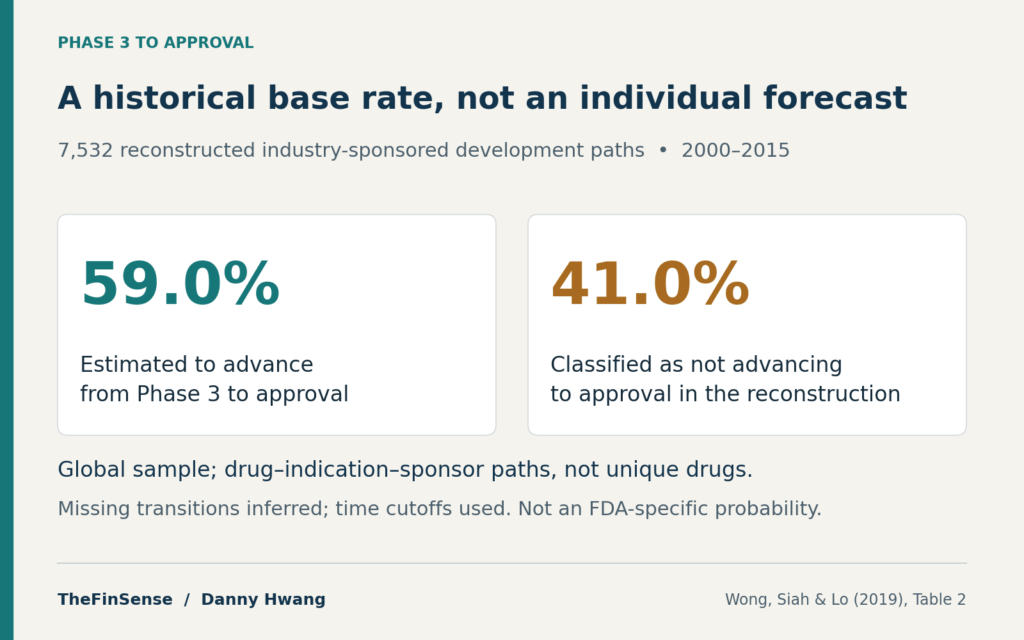
Wong, Siah and Lo estimated a 59.0% Phase 3-to-approval rate in their 2000–2015 industry dataset; 41.0% were classified as not advancing to approval. The rate swings from 35.5% in oncology to 85.4% in vaccines, so the phase label alone does not settle the historical rate. It is a historical average across global industry-sponsored development, not a forecast for the stock you own.
Browse the full guide
What Phase 3 Actually Tells You
A drug in Phase 3 has progressed through earlier safety, dose and preliminary efficacy work. Safety and efficacy are still being tested; reaching this phase is not a safety clearance. A company release may emphasize an endpoint met, while a pipeline diagram ends at a single box marked approval. That presentation can make the last step look like paperwork.
Call it the formality assumption. A simple pipeline diagram can encourage that reading. A pipeline diagram maps the regulatory sequence, and a map has to end somewhere. What it does not show is how often the last box opens.
In their 2019 journal article, Wong, Siah and Lo reconstructed 7,532 industry-sponsored Phase 3 development paths from 2000–2015 trial data. Their estimated approval rate was 59.0%, with a standard error of 0.6 percentage points. Missing transitions were inferred and termination was classified with time cutoffs, so this is an estimate from a defined dataset, not an observation of every program’s eventual fate.
The assumption is not wrong about direction. Most programs that get that far do finish. It is wrong about magnitude, and the size of the error is the whole story. Four in ten is not a tail event. It remains a substantial outcome even after a program reaches Phase 3.
What the count actually counts
The counting unit changes what the rate can tell you.
Wong, Siah and Lo count development paths, not drugs and not companies. The reconstruction distinguishes drug, disease indication and sponsor. A compound tested against three diseases can contribute multiple paths; sponsor records matter too. The 41% therefore concerns classified development paths, rather than a permanent verdict on 41% of distinct drugs.
That distinction has a practical edge. A company with four programs needs four program-level assessments. Those outcomes may share scientific, manufacturing or financing risks; this table does not establish that the bets are independent.
IN PLAIN ENGLISH:
The 59.0% describes a population of programs over sixteen years. It does not describe your drug, and it was never built to.
So how much does that population figure move once you split it?
The Same Phase, Approval Rates That Differ by 2.4x
The 59.0% average hides differences between therapeutic groups. The relevant group offers context for a holding, not its individual probability.
Wong, Siah and Lo split the same 7,532 paths into nine therapeutic groups. Vaccines finished at 85.4%. Oncology finished at 35.5%. Every one of those programs carried the identical Phase 3 label.
Phase 3 to approval, by therapeutic group
View chart data table
| Therapeutic group | Phase 3 to approval |
|---|---|
| Vaccines | 85.4% |
| Infectious disease | 75.3% |
| Ophthalmology | 74.9% |
| Genitourinary | 66.5% |
| Autoimmune / Inflammation | 63.7% |
| Cardiovascular | 62.2% |
| Metabolic / Endocrinology | 51.6% |
| CNS | 51.1% |
| Oncology | 35.5% |
Phase 3 to approval, all indications, industry-sponsored, 2000 to 2015. Paths are reconstructed drug/indication/sponsor combinations, not unique drugs. SE is the standard error.
| Therapeutic group | Paths | Approved | SE | Did not |
|---|---|---|---|---|
| Vaccines (infectious disease) | 609 | 85.4% | 1.4 | 14.6% |
| Infectious disease | 1,078 | 75.3% | 1.3 | 24.7% |
| Ophthalmology | 207 | 74.9% | 3.0 | 25.1% |
| Genitourinary | 212 | 66.5% | 3.2 | 33.5% |
| Autoimmune / Inflammation | 969 | 63.7% | 1.5 | 36.3% |
| Cardiovascular | 964 | 62.2% | 1.6 | 37.8% |
| Metabolic / Endocrinology | 1,101 | 51.6% | 1.5 | 48.4% |
| CNS | 1,156 | 51.1% | 1.5 | 48.9% |
| Oncology | 1,236 | 35.5% | 1.4 | 64.5% |
| Overall | 7,532 | 59.0% | 0.6 | 41.0% |
The nine group counts sum to 7,532. Rates, counts and standard errors in the table above correspond to the published Table 2; the final column is 100% minus the displayed approval rate.
Read the standard errors before you read the rate
The standard error column helps distinguish precision from the point estimate.
The overall 59.0% rests on 7,532 paths and carries an SE of 0.6, which is tight. Ophthalmology’s 74.9% rests on 207 paths with an SE of 3.0, and genitourinary’s 66.5% rests on 212 with an SE of 3.2. Those estimates have wider sampling uncertainty than the overall rate. Read their larger standard errors alongside the point estimates; they are not a numerical validity cutoff.
A larger standard error calls for more caution about the point estimate. It does not make the estimate unusable, and it does not capture every source of measurement or model uncertainty.
A 2019 corrigendum corrected a spreadsheet formatting error in the source paper’s tables. It touched the Phase 2 to 3 columns and the Phase 3 to approval column of Table 1, not the Table 2 group rates above.
Before you apply that row to a holding, there is a scope problem worth knowing about.
Why This Is Not Your Drug’s FDA Probability
The scope of the dataset determines which question its base rate can answer.
Three limits travel with every number on this page.
It measures regulatory approval, not FDA approval
Wong, Siah and Lo built their sample from Citeline data covering United States and non-United States sources. Approval in their table means a drug won a license from a regulator, not specifically from the FDA. If your position turns on a single United States decision, this rate is adjacent evidence rather than direct evidence.
An FDA-specific counterpart does exist, and comparing the two is more instructive than picking one. The BIO, Informa and QLS Advisors report on clinical development success covers 1 January 2011 to 30 November 2020 and restricts itself to company-sponsored programs run for FDA registration. Approval there means FDA approval, full stop.
Two published datasets, same question, different answers. Not interchangeable and not to be averaged.
| Phase 3 to approval | Wong, Siah and Lo | BIO, Informa, QLS |
|---|---|---|
| All indications | 59.0% | 52.4% |
| Oncology | 35.5% | 43.9% |
| Window | 2000 to 2015 | 2011 to 2020 |
| Regulator | Global | FDA only |
| Method | Path-by-path | Phase-by-phase |
| Counting unit | Drug/indication/sponsor path | Registration program |
Look at the oncology row, because it does something the overall row does not. The FDA-only dataset is lower on all indications and higher on oncology, 43.9% against 35.5%. Both figures are correctly transcribed from their sources. The samples, windows, counting units and arithmetic differ. This comparison does not isolate the effect of any one difference, and neither estimate is a correction of the other.
That is the whole argument of this section in one table row. A base rate is not a fact about your drug. It is a fact about a dataset, and swapping the dataset can move the number by eight percentage points in the direction you least expect. Use whichever one matches your question, name it when you quote it, and do not blend them.
Two structural notes if you go to the primary sources yourself. BIO classifies vaccines as a drug modality rather than a disease area, so there is no vaccine row to line up against the 85.4% above. And a Citeline analysis of phase transitions from 2014 to 2023 puts the overall Phase 1 to approval likelihood at 6.7%, down from BIO’s 7.9%. Both sit on the same Biomedtracker series that produced the widely quoted 10.4% in 2014 and 9.6% in 2016, but shared database lineage does not hold program composition and methods constant across reports. The 2014 to 2023 update has not been published with the full program counts the 2011 to 2020 report carries.
It is a category history, not an individual probability
A 35.5% oncology rate is what happened to 1,236 oncology programs over sixteen years. It is not the probability that your oncology drug gets approved.
Your drug has a trial design, an endpoint, a comparator, a manufacturing record and a review history, and none of those are in the table. The base rate tells you what the neighborhood looks like. It does not tell you which house you bought.
The window closed in 2015
The sample ends on 31 October 2015. Accelerated pathways, biomarker-guided trials and the review environment have all moved since. The paper itself found overall success falling from 2005 to 2013 and rising after, which is a reminder that this rate is a measurement of a period rather than a constant.
The later Citeline analysis reports a lower overall figure. Citeline’s 2014 to 2023 figures give a 55% Phase 3 transition and 92% approval on filing, which multiply to roughly 51%. Both inputs are rounded and the dataset is published without program counts, so read it as a later dataset comparison, not an isolated time trend or a replacement for the 59.0%.
In the reconstructed 2000–2015 global industry dataset, 41.0% of Phase 3 paths were classified as not advancing to regulatory approval, and the rate varied by more than a factor of two across therapeutic groups. That is a historical base rate worth knowing before a decision date. It is not an FDA-specific probability, and it is not a forecast for any individual application.
Approval rates do not describe stock-price reactions. A separate clinical-result event study addresses that different question.
How Stocks Reacted to Positive and Negative Trial Results
There is a second published asymmetry sitting underneath the first, and it points in an uncomfortable direction.
Thomas Hwang, then at Harvard, ran an event study on announcements of clinical trial results from large United States-listed biopharmaceutical companies between January 2011 and May 2013. He found 24 events, 16 positive and 8 negative. Across the three trading days from two days before the clinical-result announcement through the announcement date, CAR(-2,0), the median cumulative abnormal return was 0.8% for positive events and negative 2.0% for negative events. Extending the window through the next trading day, CAR(-2,+1), reduced the positive median to 0.4%, which was not statistically significant; the negative median remained significant. These are cumulative market-adjusted returns, not single-day stock-price changes or returns on FDA approval decisions.
Stock return underperformance due to negative events is greater in magnitude and persists longer than abnormal returns due to positive events
Thomas J. Hwang, PLOS ONE, 2013
What that finding does and does not license
It would be easy to multiply those two figures by the 59.0% approval rate and produce a tidy expected drag on a portfolio. That calculation does not hold.
Four problems break it. The events are different, since Hwang measured reactions to trial results and the 59.0% measures regulatory outcomes. The samples are different, since Hwang studied large-cap firms and the 59.0% covers global programs of every sponsor size. The statistics do not combine, because a probability-weighted blend of two conditional medians is not an expected value, and Hwang reported medians under a signed-rank test precisely because the sample was too small for parametric estimates. And 24 events is not enough to support a portfolio-level projection in any case.
So this page does not run that arithmetic. What survives is the direction, and the direction is still useful.
The two medians sit roughly two and a half to one against the holder. That ratio is a property of Hwang’s small sample of large-cap announcements, not a portfolio drag and not a forecast. It illustrates asymmetric cumulative reactions in that sample. It does not establish the size or direction of the next announcement-day move.
One related finding points the same way without closing the gap. Cho, Singh and Lo analyzed news reactions across a much larger set of biopharma firms and reported that smaller companies tend to move more sharply on product-development news than larger ones. Hwang’s sample was large-cap. A concentrated small-cap holding is not the population he measured, and that is a reason for caution rather than a number to substitute in.
Which leaves the only part of this you can actually act on.
How to Look Up Your Own Holding
Everything above is background until you run it against a ticker. Use these checks before a decision date, and revisit them when trial, regulatory or financing facts change.
Rosa is 41 and reads Phase 3 data for a living as a hospital pharmacist. She can read a Kaplan-Meier curve without slowing down. A decision date for a drug she already owns sits on her calendar. She opens the Positions tab, where the ticker sits above a line reading Today’s change, and that line has never once shown her the denominator she reads every week at work.
Rosa is a hypothetical composite, not a real individual.
Six checks before a decision date
- Find the indication, not the drug. Search the company on ClinicalTrials.gov and read the Conditions field on the Phase 3 record, or open the indication column of the company’s pipeline page. That phrase is what maps to a row in the table above.
- Read the row, then read its standard error. Use the standard error, in percentage points, to judge sampling uncertainty alongside the rate. There is no universal SE cutoff that turns an estimate into a reliable forecast.
- Check whether this is a first review or a resubmission. A program returning after a complete response letter is in a different situation from one arriving for the first time, and the historical base rate does not separate the two.
- Find out what kind of deficiency is at issue, if one is known. A manufacturing or labeling problem and a request for another trial are both complete response letters. They are not the same event for a shareholder.
- Work out how much cash a delay costs. Wong, Siah and Lo found terminated Phase 3 trials concluded about 3.2 months after advanced ones, which flips the sign from Phase 2, where terminated trials end 8.1 months sooner. A Phase 3 program running long is not the reassurance it reads like, and on a single-asset balance sheet those months are burn. That is closer to a solvency question than a regulatory one.
- Size the position to one bad morning. These studies do not establish a suitable position-size percentage for an individual portfolio. The workable test is whether a single decision going against you would force a decision you do not want to make.
Two habits keep check six from being re-argued every time a decision date lands. Write the group rate and the size limit into an investment policy statement before you need them, and let a rebalancing strategy pull the position back when a good year stretches it past what you agreed to.
How much of this reaches you depends on the wrapper
The same program risk reaches a portfolio differently through a single stock, a sector fund or a broad index.
If you hold one biotech name, a drug-specific decision can affect the whole position; the therapeutic-group rate does not determine the size of that position. If you hold a sector fund, dozens of programs sit inside the basket and one complete response letter is diluted rather than removed. If you own large-cap pharma inside a broad index, diversification generally reduces the effect of one program, although its portfolio impact still depends on the holding weight and market reaction.
That choice of wrapper is an asset allocation decision made well before any drug-specific odds apply, and the ETFs versus mutual funds question decides the tax and trading detail on top of it.
The obvious objection is that the market already knows all of this. It probably does, at least in aggregate. But an efficient price for the sector’s average program is not the same as the right position size for a specific holding whose published category rate is 35.5%. Nothing here is an edge over the market. It is a check on how much of your own money is standing on one row of a table.
Which row is yours?
Common Questions
Is FDA approval guaranteed after Phase 3?
No. Wong, Siah and Lo estimated 59.0% approval across 7,532 reconstructed industry-sponsored Phase 3 paths in their 2000–2015 dataset; 41.0% were classified as not advancing to approval. Two caveats matter. The reconstructed paths distinguish drug, disease indication and sponsor, rather than counting unique drugs. And the sample covers global regulators rather than the FDA alone, so it is a useful reference point for a United States decision rather than a direct measurement of one.
How often do Phase 3 drugs get approved?
The published overall figure is 59.0%, with a standard error of 0.6 on 7,532 development paths. It is not one number in practice. Oncology programs finished at 35.5% and vaccine programs at 85.4%, a spread of more than a factor of two across the same phase label. Hay and colleagues, working from a different database over 2003 to 2011, reported a 60.1% Phase 3-to-filing transition rate and an 83.2% filing-to-approval rate for all indications. Their Table 4 also directly reports a 50.0% Phase 3 likelihood of approval, consistent with multiplying the two rounded transition rates, on an FDA-based path rather than a global one, which is a reminder that this rate is measured rather than known.
What exactly is a complete response letter?
A complete response letter means the FDA will not approve an application in its current review cycle because of deficiencies it has identified. It is not necessarily a permanent refusal. A sponsor can address the deficiencies and resubmit, and many do. The economic weight of a letter therefore depends on what it asks for. A labeling or manufacturing fix and a demand for an additional trial are both complete response letters, and they are very different events for a shareholder, particularly one holding a company with a single asset and limited cash.
Should I sell before a PDUFA date?
This page does not give that answer, but two facts are worth having first. A PDUFA date is the FDA’s performance goal date for acting on an application, not a guaranteed decision day, and timelines can extend. Hwang’s separate study of clinical-result announcements found asymmetric cumulative abnormal returns in a small large-cap sample; it did not estimate returns around PDUFA dates. It supplies no trading rule for a regulatory decision. Consider the consequences of an adverse outcome for your whole portfolio before choosing a position size. If a sale does happen at a loss, the tax loss harvesting rules cover what a taxable account may do next.
Why did the stock fall on an approval?
A regulatory approval does not by itself determine the stock return. To explain a specific fall, compare what was announced with prior expectations and check other news released at the same time. Hwang’s study cannot identify the cause: it examined clinical trial results, not FDA approval decisions. Its 0.8% and negative 2.0% medians are cumulative abnormal returns from two trading days before the trial-result announcement through the announcement date, CAR(-2,0), in 24 events at large firms during 2011-2013. They are neither single-day returns nor a forecast for your holding.
The Bottom Line
Wong, Siah and Lo published a historical estimate, not a forecast: 59.0% approval across the reconstructed Phase 3 paths in their sixteen-year sample.
What that count is good for is narrow and real. It tells you the last box on the pipeline chart opens about six times in ten, and that the figure moves from roughly a third to roughly six in seven depending on the disease. What it is not good for is predicting a specific application, which is a limit worth carrying rather than arguing with.
Two published numbers, then. The base rate says the odds vary by more than double across the same phase. The event study found a larger negative than positive median cumulative abnormal return in its small clinical-result sample. Neither result forecasts an FDA-decision return or shows that the market has failed to price the risk. Use them to frame the uncertainty, not to claim a trading edge.
Open your biotech holding and find the indication. If it reads oncology, the two published datasets put the historical Phase 3 rate at 35.5% and 43.9% depending on which one you ask, and both of those have been in print for years. Either can frame the historical context, provided you keep its population and limitations attached.
Your turn. Which therapeutic group is your biotech holding in, and did you know the number before today?
- Wong, Siah and Lo (2019), Table 2
- Corrigendum to Wong, Siah and Lo
- BIO, Informa and QLS (2021)
- Citeline: clinical development success rates, 2014–2023
- Hwang (2013): clinical-result event study
- Cho, Singh and Lo (2024): biopharma news study
- Hay et al. (2014), Table 4
What is measured. All nine therapeutic-group rates, path counts and standard errors come from Table 2 of Wong, Siah and Lo (2019). The reconstruction traces drug/indication/sponsor combinations and uses inferred missing transitions and time-based termination rules, including a 900-day Phase 3 threshold. It does not observe every program indefinitely. The sample is industry-sponsored programs from 1 January 2000 to 31 October 2015, drawn from Citeline data covering United States and non-United States sources. Approval means regulatory approval, not FDA approval specifically.
Second dataset. The FDA-only comparison figures come from BIO, Informa Pharma Intelligence and QLS Advisors, Clinical Development Success Rates and Contributing Factors 2011-2020, covering 1 January 2011 to 30 November 2020 across 12,728 phase transitions from 9,704 company-sponsored, FDA registration-enabling programs at 1,779 companies. That report uses phase-by-phase compounding: Phase 3 to filing of 57.8% multiplied by filing to approval of 90.6% gives the 52.4% quoted above. Oncology Phase 3 to approval is 43.9%. The two datasets are reported side by side and never combined.
Prior estimates. Hay and colleagues (2014), Table 4, all-indications row, directly report a 50.0% Phase 3 likelihood of approval. Their 60.1% Phase 3-to-filing rate uses 975 resolved transitions, and their 83.2% filing-to-approval rate uses 659. Multiplying the rounded rates gives 50.0032%, consistent with the displayed 50.0%. The broader 2003–2011 BioMedTracker sample contains 7,372 paths; it is not the denominator of either phase rate. That is the same compounding used for the BIO figure above, and it produces an FDA-based rather than a global rate. The Citeline 2014 to 2023 figures quoted in the scope limits, a 55% Phase 3 transition and 92% approval on filing, are published rounded and without program counts, so the roughly 51% product carries no standard error and is reported as a direction only.
What is not calculated. This page deliberately does not combine the 59.0% approval rate with published announcement returns to produce an expected portfolio drag. The two figures measure different events on different samples, and a probability-weighted blend of two conditional medians is not an expected value. An earlier draft of this article carried such a model and it has been removed.
Event-study figures. Hwang (2013) reports CAR(-2,0) medians spanning two trading days before the announcement through the announcement date, under a Wilcoxon signed-rank test on 24 clinical-result announcements from large United States-listed firms between January 2011 and May 2013. Small-sample medians describe that sample. They are not population parameters.
Regulatory source. In its September 4, 2025 announcement, the FDA described a real-time complete-response-letter publication policy. That announcement is dated background, not evidence that every current letter is public. Check the FDA’s current record and the company’s filing for the specific application; absence from a public list does not establish that an application has no deficiencies.
Update history
- Date correction2026-11-01CORRECTION
Marked the existing last-reviewed date (October 17, 2026) as a machine-readable date and updated the author title. No analysis, figure, or source changed.
- Independent-check clarificationOctober 17, 2026CLARIFICATION
Limited the opening inference to the observed differences among Phase 3 therapeutic groups, labeled the 2.4x comparison as an approval-rate ratio, and separated approval probabilities from stock-price reactions. Published source values and all quantitative assets are unchanged.
- Article clarificationOctober 17, 2026CLARIFICATION
Replaced the one-time position check with event-driven rechecks, distinguished therapeutic-group context from individual probability and position size, qualified dataset comparisons and broad-index risk, and removed unsupported competitor-page and private-disclosure assertions. Preserved all research data, the chart and the three-page worksheet.
- 2026-10 verification2026-10-15CORRECTION
Verified Hay et al. Table 4 and corrected 50.0% to a directly reported likelihood of approval. Clarified phase denominators, reconstructed program statuses, continuing safety assessment and standard-error interpretation. Therapeutic-group data remain unchanged.
- 2026-10 repair2026-10-15CORRECTION
Clarified that the event-study returns span two trading days before a clinical-result announcement through its date, rather than a single day or an FDA decision. Corrected the three-page worksheet description and layout, and replaced an unconfirmed regulatory timeline with dated FDA guidance.
- v1.127 July 2026CORRECTIONTwo unattributed figures sourced. 50.0% traced to Hay et al. (2014) and labelled as derived at that time. Citeline 2014-2023 LOA attributed and extended to the Phase 3 step. 8 sources.
- v1.026 July 2026PUBLISHOriginal publication. 6 sources at publish. 4010 words.